Connect with us

health and wellness

US health care is rife with high costs and deep inequities, and that’s no accident

Published

on

Last Updated on July 20, 2025 by Daily News Staff

A public health historian explains how the system was shaped to serve profit and politicians

health care
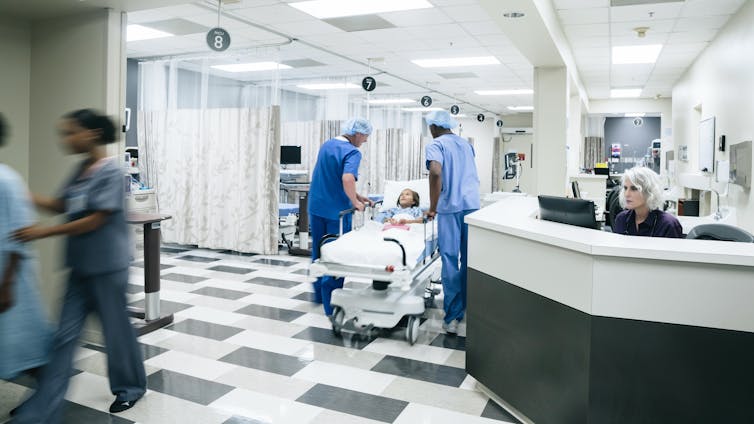
Concessions to the private sector are one reason why health care is so costly.
FS Productions/Tetra images via Getty Images

Zachary W. Schulz, Auburn University

A few years ago, a student in my history of public health course asked why her mother couldn’t afford insulin without insurance, despite having a full-time job. I told her what I’ve come to believe: The U.S. health care system was deliberately built this way.

People often hear that health care in America is dysfunctional – too expensive, too complex and too inequitable. But dysfunction implies failure. What if the real problem is that the system is functioning exactly as it was designed to? Understanding this legacy is key to explaining not only why reform has failed repeatedly, but why change remains so difficult.

I am a historian of public health with experience researching oral health access and health care disparities in the Deep South. My work focuses on how historical policy choices continue to shape the systems we rely on today.

By tracing the roots of today’s system and all its problems, it’s easier to understand why American health care looks the way it does and what it will take to reform it into a system that provides high-quality, affordable care for all. Only by confronting how profit, politics and prejudice have shaped the current system can Americans imagine and demand something different.

Decades of compromise

My research and that of many others show that today’s high costs, deep inequities and fragmented care are predictable features developed from decades of policy choices that prioritized profit over people, entrenched racial and regional hierarchies, and treated health care as a commodity rather than a public good.

Over the past century, U.S. health care developed not from a shared vision of universal care, but from compromises that prioritized private markets, protected racial hierarchies and elevated individual responsibility over collective well-being.

Employer-based insurance emerged in the 1940s, not from a commitment to worker health but from a tax policy workaround during wartime wage freezes. The federal government allowed employers to offer health benefits tax-free, incentivizing coverage while sidestepping nationalized care. This decision bound health access to employment status, a structure that is still dominant today. In contrast, many other countries with employer-provided insurance pair it with robust public options, ensuring that access is not tied solely to a job.

In 1965, Medicare and Medicaid programs greatly expanded public health infrastructure. Unfortunately, they also reinforced and deepened existing inequalities. Medicare, a federally administered program for people over 64, primarily benefited wealthier Americans who had access to stable, formal employment and employer-based insurance during their working years. Medicaid, designed by Congress as a joint federal-state program, is aimed at the poor, including many people with disabilities. The combination of federal and state oversight resulted in 50 different programs with widely variable eligibility, coverage and quality.

[youtube https://www.youtube.com/watch?v=0RR-Q8D131s?wmode=transparent&start=0]
A brief history of Medicaid expansion.

Southern lawmakers, in particular, fought for this decentralization. Fearing federal oversight of public health spending and civil rights enforcement, they sought to maintain control over who received benefits. Historians have shown that these efforts were primarily designed to restrict access to health care benefits along racial lines during the Jim Crow period of time.

Advertisement
Get More From A Face Cleanser And Spa-like Massage

Bloated bureaucracies, ‘creeping socialism’

Today, that legacy is painfully visible.

States that chose not to expand Medicaid under the Affordable Care Act are overwhelmingly located in the South and include several with large Black populations. Nearly 1 in 4 uninsured Black adults are uninsured because they fall into the coverage gap – unable to access affordable health insurance – they earn too much to qualify for Medicaid but not enough to receive subsidies through the Affordable Care Act’s marketplace.

The system’s architecture also discourages care aimed at prevention. Because Medicaid’s scope is limited and inconsistent, preventive care screenings, dental cleanings and chronic disease management often fall through the cracks. That leads to costlier, later-stage care that further burdens hospitals and patients alike.

Meanwhile, cultural attitudes around concepts like “rugged individualism” and “freedom of choice” have long been deployed to resist public solutions. In the postwar decades, while European nations built national health care systems, the U.S. reinforced a market-driven approach.

Publicly funded systems were increasingly portrayed by American politicians and industry leaders as threats to individual freedom – often dismissed as “socialized medicine” or signs of creeping socialism. In 1961, for example, Ronald Reagan recorded a 10-minute LP titled “Ronald Reagan Speaks Out Against Socialized Medicine,” which was distributed by the American Medical Association as part of a national effort to block Medicare.

The health care system’s administrative complexity ballooned beginning in the 1960s, driven by the rise of state-run Medicaid programs, private insurers and increasingly fragmented billing systems. Patients were expected to navigate opaque billing codes, networks and formularies, all while trying to treat, manage and prevent illness. In my view, and that of other scholars, this isn’t accidental but rather a form of profitable confusion built into the system to benefit insurers and intermediaries.

[youtube https://www.youtube.com/watch?v=KqBAIPKS2pk?wmode=transparent&start=0]
President Donald Trump’s proposed cuts would reduce Medicaid spending by about US$700 billion.

Coverage gaps, chronic disinvestment

Even well-meaning reforms have been built atop this structure. The Affordable Care Act, passed in 2010, expanded access to health insurance but preserved many of the system’s underlying inequities. And by subsidizing private insurers rather than creating a public option, the law reinforced the central role of private companies in the health care system.

The public option – a government-run insurance plan intended to compete with private insurers and expand coverage – was ultimately stripped from the Affordable Care Act during negotiations due to political opposition from both Republicans and moderate Democrats.

When the U.S. Supreme Court made it optional in 2012 for states to offer expanded Medicaid coverage to low-income adults earning up to 138% of the federal poverty level, it amplified the very inequalities that the ACA sought to reduce.

These decisions have consequences. In states like Alabama, an estimated 220,000 adults remain uninsured due to the Medicaid coverage gap – the most recent year for which reliable data is available – highlighting the ongoing impact of the state’s refusal to expand Medicaid.

Advertisement
Get More From A Face Cleanser And Spa-like Massage

In addition, rural hospitals have closed, patients forgo care, and entire counties lack practicing OB/GYNs or dentists. And when people do get care – especially in states where many remain uninsured – they can amass medical debt that can upend their lives.

All of this is compounded by chronic disinvestment in public health. Federal funding for emergency preparedness has declined for years, and local health departments are underfunded and understaffed.

The COVID-19 pandemic revealed just how brittle the infrastructure is – especially in low-income and rural communities, where overwhelmed clinics, delayed testing, limited hospital capacity, and higher mortality rates exposed the deadly consequences of neglect.

A system by design

Change is hard not because reformers haven’t tried before, but because the system serves the very interests it was designed to serve. Insurers profit from obscurity – networks that shift, formularies that confuse, billing codes that few can decipher. Providers profit from a fee-for-service model that rewards quantity over quality, procedure over prevention. Politicians reap campaign contributions and avoid blame through delegation, diffusion and plausible deniability.

This is not an accidental web of dysfunction. It is a system that transforms complexity into capital, bureaucracy into barriers.

Patients – especially the uninsured and underinsured – are left to make impossible choices: delay treatment or take on debt, ration medication or skip checkups, trust the health care system or go without. Meanwhile, I believe the rhetoric of choice and freedom disguises how constrained most people’s options really are.

Other countries show us that alternatives are possible. Systems in Germany, France and Canada vary widely in structure, but all prioritize universal access and transparency.

Understanding what the U.S. health care system is designed to do – rather than assuming it is failing unintentionally – is a necessary first step toward considering meaningful change.

Zachary W. Schulz, Senior Lecturer of History, Auburn University

This article is republished from The Conversation under a Creative Commons license. Read the original article.

Advertisement
Get More From A Face Cleanser And Spa-like Massage

Child Health

Changing the Landscape of Childhood Cancer Survivorship

Childhood Cancer: hile “cancer” is a term no family wants to hear, especially when it comes to their children, there is reason for hope. Today, 85% of children diagnosed with cancer survive at least five years. Survival is only part of the journey, however.

Published

on

Changing the Landscape of Childhood Cancer Survivorship

Changing the Landscape of Childhood Cancer Survivorship

(Feature Impact) While “cancer” is a term no family wants to hear, especially when it comes to their children, there is reason for hope. Today, 85% of children diagnosed with cancer survive at least five years, according to the National Cancer Institute, up from 75% three decades ago.

Watch this video to learn more

https://youtube.com/watch?v=GbyX36_Bkh8%3Fsi%3D9xZsTd-CgnppVKym%26controls%3D0

“This progress is driven in large part by dedicated research,” Hyundai Hope on Wheels Board Member Kevin Reilly said. “Over the last 28 years, Hyundai Hope on Wheels has committed over $300 million in pediatric cancer research and program grants, awarding more than 1,600 grants to 210 medical institutions nationwide, impacting thousands of young lives each year.”

Survival is only part of the journey, however. Nearly half (46%) of U.S. adults believe a child ringing the hospital bell after cancer treatment means the child is cancer-free and their medical journey is largely over, according to a survey conducted by Atomik Research on behalf of Hyundai Hope on Wheels. For the children and families living through a diagnosis, the reality is far more complex.

“The reality is that healing continues long after treatment, which is why sustained investment in survivorship care is a priority for us,” said John Guastaferro, executive director of Hyundai Hope on Wheels.

Isabella Franco-Capps, 11, understands that journey firsthand. Diagnosed with B-cell acute lymphoblastic leukemia at age 5, her journey took two years before she could say she’s “a cancer survivor.”

“I was diagnosed with b-cell acute lymphoblastic leukemia,” she said. “This began my two-year-long journey of scans, pokes, chemotherapy and hospital stays. And now I’m a cancer survivor.”

Fellow Hyundai Hope on Wheels National Youth Ambassador, Jackson Trihn, 12, is using his voice to call for continued research and to bring hope to others.

The role … is being able to share my story,” he said. “Not just to spread awareness but to spread hope to kids that need it. And awareness is so important because people don’t understand how hard pediatric cancer can be.”

Continued progress can help ensure more children ring the bell and receive the care and support they need long after they’ve had the opportunity to do so. To learn more about these efforts and how you can help, visit HyundaiHopeOnWheels.org. collect?v=1&tid=UA 482330 7&cid=1955551e 1975 5e52 0cdb 8516071094cd&sc=start&t=pageview&dl=http%3A%2F%2Ftrack.familyfeatures track

SOURCE:

Hyundai Hope on Wheels

💪 Your health journey starts here! Explore the latest health news, fitness tips, wellness trends, and healthy living advice. Share your thoughts in the comments and subscribe to the STM Daily News newsletter to stay informed and inspired every day.

Advertisement
Get More From A Face Cleanser And Spa-like Massage

Continue Reading

Health

Culturally Relevant Cardiovascular Disease Prevention and Care Strategies

Published

on

Culturally Relevant Cardiovascular Disease Prevention and Care Strategies

(Feature Impact) Driven by rising rates of obesity, diabetes, high blood pressure and other risk factors,cardiovascular disease has surpassed cancer as the leading cause of death among Hispanic adults in the United States.

Hispanic people represent nearly 1 in 5 of the U.S. population and are the nation’s largest ethnic minority group, yet many continue to face barriers to achieving heart health and accessing high-quality healthcare. A new scientific statement published in the American Heart Association’s flagship journal, “Circulation,” revealed how social, economic, cultural and environmental factors contribute to persistent disparities in cardiovascular health, calling for culturally tailored prevention strategies, equitable access to care and greater representation of Hispanic populations in cardiovascular research.

“Hispanic populations in the U.S. are incredibly diverse even within their own communities with differences in genetic ancestry, language, cultural traditions and social experiences that can significantly influence cardiovascular health,” said Johanna Contreras, M.D., M.Sc., FAHA, director of the Division of Heart Failure and medical director of the Hispanic Heart Center within the Mount Sinai Health System. “Yet Hispanic people remain underrepresented overall in the research that guides prevention and treatment strategies… Without better representation and more detailed data, we risk overlooking important differences that can help us improve care and save lives.”

Hispanic Cardiovascular Health by the Numbers

Cardiovascular risk factors – obesity (nearly 46%), type 2 diabetes (15.5%) and high blood pressure (approximately 44%) – are prevalent among Hispanic adults and often emerge at younger ages and occur more frequently among Hispanic adults compared with white adults.

According to the report, only about 1 in 5 Hispanic adults achieves ideal cardiovascular health as defined by the American Heart Association’s original Life’s Simple 7 metrics. Updated analyses using the Life’s Essential 8 framework demonstrated persistent disparities for heart and brain health, as well as suboptimal dietary quality, sleep patterns and levels of physical activity.

Social and Economic Barriers Matter

Biology alone does not explain cardiovascular health disparities. The environments where people live, work and age, along with social and economic challenges, impact heart health. In fact, approximately 17% of Hispanics live below the federal poverty threshold, compared with 8.2% of white adults.

“Many Hispanic adults face obstacles that extend far beyond the doctor’s office,” Contreras said. “Limited health insurance coverage, language differences, food insecurity, environmental exposures and concerns related to immigration status can make it more difficult to prevent disease, manage chronic conditions and receive timely treatment.”

Contreras emphasized the cultural values and practices of Hispanic people also influence how they perceive their health and healthcare options.

“Family plays a central role in many Hispanic communities and can be an extraordinary source of strength, support and resilience,” Contreras said. “At the same time, family members are often called upon to translate medical information, navigate health systems and help make healthcare decisions for loved ones. Those responsibilities can shape how health information is understood and acted upon.”

An Action Plan for Improving Hispanic Health

There are practical opportunities to achieve equitable cardiovascular health and reduce disparities through community engagement, culturally responsive care, inclusive research and policies that address the underlying drivers of health.

“Reducing cardiovascular disease among Hispanic populations demands action at every level,” Contreras said, “from improving access to culturally responsive care and expanding research participation to addressing the social and environmental conditions that shape health.”

Advertisement
Get More From A Face Cleanser And Spa-like Massage

By addressing both medical risk factors and the social conditions that shape health, experts believe there is an important opportunity to reduce disparities and help more people live longer, healthier lives. Learn more at Heart.org.

Photo courtesy of Shutterstock collect?v=1&tid=UA 482330 7&cid=1955551e 1975 5e52 0cdb 8516071094cd&sc=start&t=pageview&dl=http%3A%2F%2Ftrack.familyfeatures track

SOURCE:

American Heart Association

Subscribe to our news letter STM Daily News

Continue Reading

Food and Beverage

Beyond Protein: 2 Nutrients Your Plate Might Be Missing

Nutrients: Everyone is talking about protein these days whether watching their weight or managing a disease like type 2 diabetes. However, fiber and healthy fats are nutrients many people are overlooking. One food that makes it easier to invest in your health, according to nutrition experts: avocados.

Published

on

Beyond Protein: 2 Nutrients Your Plate Might Be Missing

Beyond Protein: 2 Nutrients Your Plate Might Be Missing

(Feature Impact) Everyone is talking about protein these days whether watching their weight or managing a disease like type 2 diabetes. However, fiber and healthy fats are nutrients many people are overlooking. The latest reports show most Americans already meet or exceed recommendations for protein while nearly all (about 95%) do not eat enough fiber, and many people consume too much saturated fat versus unsaturated fat, according to the 2025 Dietary Guidelines Advisory Committee. Prioritizing ways to get more fiber and healthy fats on your plate could be key to managing weight and type 2 diabetes goals this summer. 

One food that makes it easier to invest in your health, according to nutrition experts: avocados.

A growing body of research and materials from Avocados – Love One Today, a science-based resource, suggests fresh avocados offer weight management benefits, help with type 2 diabetes management and are good for blood sugar management.

17994 D embed4According to a study* of more than 27,000 adults published in the journal “Internal Medicine Review,” people who ate just over half of an avocado per day weighed 7.5 pounds less, had smaller waist sizes and tended to have healthier overall eating habits, including higher intakes of fiber and healthy fats, compared to people who didn’t eat avocados. Among the list of benefits, this delicious and healthy fruit uniquely contains fiber and healthy fats in each nutrient-dense bite which slows digestion, helping you feel satisfied and fuller longer which can help you consume fewer calories overall. In fact, if you’re using a GLP-1, avocados are one of the foods to add to your menu to make small meals feel more filling and satisfying while supporting nutrient needs.  

Scientists also recently took a second look at the largest study* about avocado consumption to-date involving close to 1,000 adults, per the journal “Current Developments in Nutrition,” and found that consistently eating one avocado every day for six months (no other diet changes required) significantly reduced dietary glycemic load (GL) by nearly 14 points, a metric that evaluates how what you are eating is affecting your blood sugar levels. GL may be an important consideration in the management of chronic diseases like type 2 diabetes. By slowing digestion, fiber and healthy fats also support stable blood sugar levels.

There are many ways to enjoy avocados, including chopped, sliced, mashed, blended, in baked goods or even frozen. Avocados add flavor, variety and nutrition across the day.

Try these recipes for Avocado and Blueberry Chia Pudding, Avocado Breakfast Bowl with Leafy Greens for your next breakfast or snack.

*Remember: Small, consistent food choices can add up over time. Research suggests regularly eating avocados may support weight management and blood sugar targets while providing the fiber and healthy fats that many Americans are overlooking. These studies were supported by the Avocado Nutrition Center. While these findings are encouraging, the studies highlighted show an association, not cause and effect, and thus more research is needed to confirm these findings in other populations.

To explore evidence-based avocado nutrition information, along with practical tips and easy recipes, visit Avocados – Love One Today, a leading resource for avocado nutrition information.

17994 detail embed1

Avocado and Blueberry Chia Pudding 

  • 1 1/2    cups plain, unsweetened soy milk (or milk of choice) 
  • 1          ripe, fresh avocado, halved, pitted and peeled 
  • 3/4       cup frozen blueberries 
  • 1/2       cup unsweetened vanilla Greek yogurt 
  • 1          tablespoon maple syrup 
  • 1/3       cup chia seeds 

To Serve: 

  • 1/3       cup granola  
  • 1/3       cup fresh blueberries 
  • 1          kiwi, chopped 
  • 1/2       fresh, ripe avocado, halved, pitted, peeled and chopped 
  1. In blender, puree soy milk, avocado, blueberries, yogurt and maple syrup until smooth. Pour mixture into storage container or bowl and add chia seeds. Whisk well to combine. Cover with lid or plastic wrap and refrigerate 4 hours or overnight, until thickened.
  2. To serve, divide into bowls and top with granola, fresh blueberries, kiwi and avocado. 
  3. Notes: Use any milk (dairy or non-dairy) that you prefer in pudding. Use fresh blueberries or conventional frozen blueberries. Other topping options include: nuts, seeds, hemp hearts, sliced banana or strawberries, or nut butter. 
17994 detail embed2

Avocado Breakfast Bowl with Leafy Greens

Bowl: 

  • 1          medium sweet potato, chopped (about 1 3/4 cup) 
  •             nonstick cooking spray
  • 1/4       teaspoon smoked paprika 
  • 1/4       teaspoon garlic powder 
  • 1/4       teaspoon salt 
  • 1/2       cup quinoa 
  • 1          cup water, plus additional for boiling eggs, divided  
  • 2          eggs 
  • 2          cups arugula 
  • 1          ripe, fresh avocado, halved, pitted, peeled and chopped 
  • 1/4       cup pickled red onions 

Avocado Tahini Dressing: 

  • 1/2       large avocado 
  • 1/4       cup tahini 
  • 1          lemon, juice only (2 tablespoons) 
  • 3/4       cup water 
  • 1          tablespoon fresh chives 
  • salt, to taste 
  • pepper, to taste
  1. Preheat oven to 400 F. Add chopped sweet potato to baking sheet. Spray with cooking oil then add smoked paprika, garlic powder and salt. Toss to coat in spices. Bake 22-25 minutes, or until tender.
  2. In medium saucepan, add quinoa and water. Bring to simmer and cover, cooking 12-15 minutes, or until quinoa is tender and fluffy.
  3. Fill small saucepan with water and bring to boil. Use slotted spoon to lower eggs into water. Cook 8 minutes then transfer eggs to bowl of ice water to cool before peeling.
  4. To make dressing: In small blender, puree avocado, tahini, lemon juice, water and fresh chives until smooth. Add more water, 1 tablespoon at a time, if needed, to thin until pourable. Season with salt and pepper, to taste.
  5. Assemble bowls, each with 1/2 sweet potato, 1/2 cup quinoa, 1 egg, 1 cup arugula, 1/2 avocado, 2 tablespoons pickled red onion and 3 tablespoons dressing. Reserve remaining dressing in refrigerator.
17994 detail embed3

Heart-Healthy Frozen Avocado Banana Paleta 

  • 1          ripe, fresh avocado, halved, pitted, peeled and diced 
  • 4          cups orange juice 
  • 2          medium bananas, peeled and sliced 
  • 1          tablespoon lime juice 
  • 8          paper cups (5 ounces)
  • 8          wooden craft sticks 
  1. In blender, blend avocado, orange juice, bananas and lime juice on high until smooth. Divide into paper cups. Cover cups with aluminum foil. Insert one stick through center of each foil. Freeze 4 hours until firm. 
collect?v=1&tid=UA 482330 7&cid=1955551e 1975 5e52 0cdb 8516071094cd&sc=start&t=pageview&dl=http%3A%2F%2Ftrack.familyfeatures
track

SOURCE:

Avocados – Love One Today

🍴 What’s your favorite food, recipe, or dining spot? Tell us in the comments! Then subscribe to the STM Daily News newsletter for fresh recipes, restaurant news, food trends, and delicious stories delivered straight to your inbox. Join our growing community of food lovers today!

Advertisement
Get More From A Face Cleanser And Spa-like Massage

Continue Reading

Trending










